
Choosing between DHI and FUE hair transplant can be confusing because both methods use your own hair follicles but differ in how grafts are placed. The comparison should look beyond technique names and consider the donor area, hair-loss pattern, desired density, procedure time, and recovery expectations. Neither approach guarantees a specific result, and suitability varies from person to person. This guide explains the practical differences between DHI and FUE, how each procedure is performed, and what recovery may involve. A qualified hair restoration professional can assess your scalp and help determine which option fits your needs.
What Are the Main Differences Between DHI and FUE?
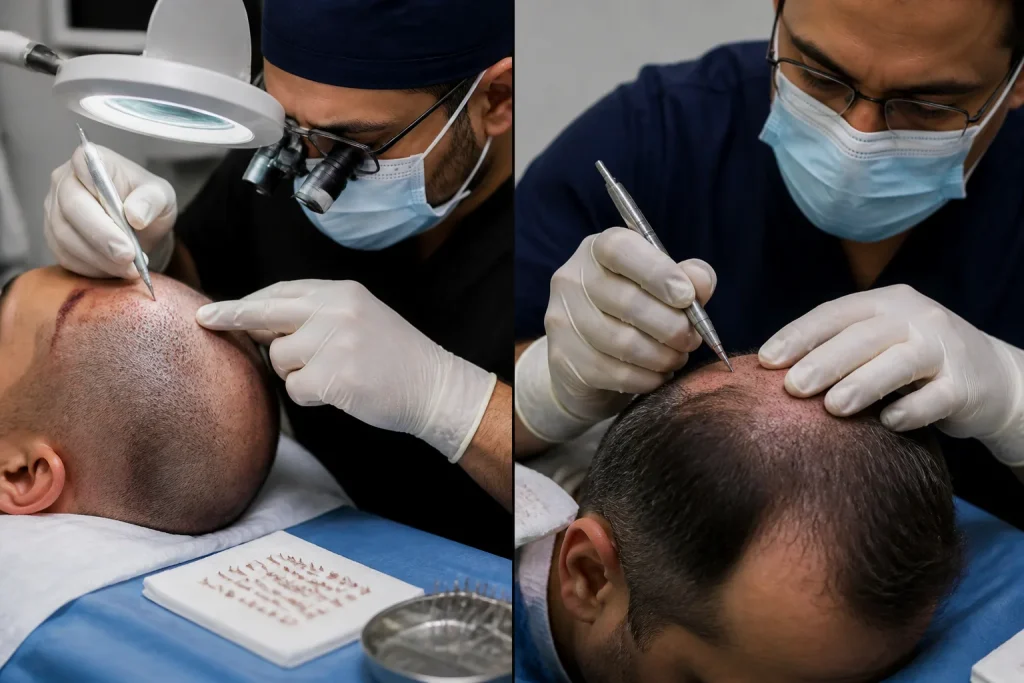
DHI and FUE are closely related hair restoration techniques because both use individual follicular units, usually harvested from a donor area and placed into areas affected by hair loss. The main distinction is how the grafts are implanted after extraction. In a conventional FUE workflow, the surgeon or clinical team creates tiny recipient channels before placing the grafts into them. This allows the direction, angle, and distribution of the transplanted hair to be planned as part of a separate step.
DHI uses a specialized implanter pen to load and insert each graft directly into the recipient area. Because channel creation and graft placement occur in one movement, the process may offer precise control over placement in suitable cases. However, DHI is not a completely different form of follicular-unit transplantation, and the quality of the result still depends on surgical planning, graft handling, donor supply, and the condition of the recipient area.
Direct implantation is therefore the clearest practical difference, rather than a guarantee that one method is superior. Clinics may also use different protocols or combine elements of both approaches, so terminology is not always consistent. A technique name alone cannot determine the right treatment; hair-loss pattern, desired density, available grafts, and the practitioner’s experience must also be assessed.
How Do Graft Extraction and Implantation Compare?
Graft handling begins in the donor area, where individual follicular units are identified and removed with a small punch during FUE-based extraction. The surgeon must consider follicle direction, tissue characteristics, hair caliber, and the risk of transection, which occurs when a follicle is damaged during removal. Careful extraction helps preserve graft quality and leaves the donor region suitable for a natural appearance.
After harvesting, the grafts are examined, sorted, and kept in a controlled solution until placement. In conventional FUE implantation, the surgeon creates recipient-site incisions before inserting the grafts with forceps or another instrument. DHI uses a loaded implanter pen to place the follicle directly into the recipient area, combining incision creation and insertion in one movement. The choice of approach depends on the surgeon’s technique, the patient’s anatomy, and the planned design.
Graft placement angle and direction are central to a natural-looking result. Follicles near the hairline usually require carefully varied angles and spacing, while existing hair must be respected to reduce trauma. Graft quality, the number of hairs per follicular unit, and the available donor supply also affect achievable density. Neither method automatically produces greater density in every patient.
Procedure length varies with the number of grafts, the size of the treatment area, extraction speed, and the need for detailed placement. A clinic should assess the patient individually rather than promise a fixed graft number or treatment duration, since excessive harvesting can compromise donor-area appearance.
Which Technique Suits Different Hair Loss Patterns?
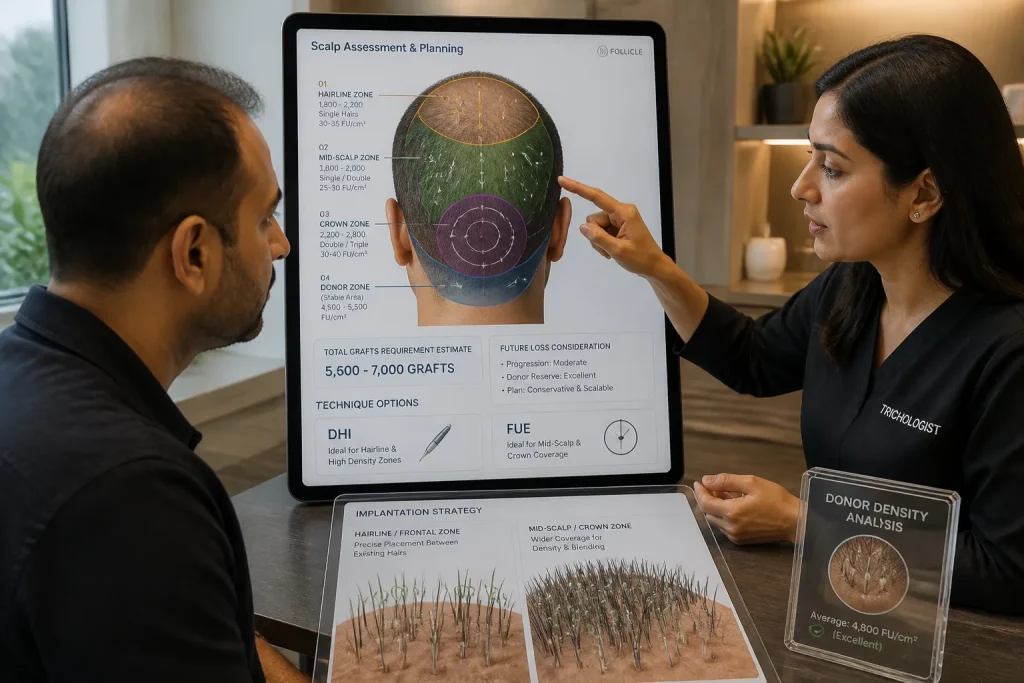
The most suitable hair transplant approach depends largely on where thinning occurs and how much stable donor hair is available. A receding hairline may require carefully controlled placement between existing hairs, while crown restoration often involves a broader area and a different distribution of grafts. Neither DHI nor FUE is automatically better for every pattern.
Diffuse thinning can be more complex because native hair remains throughout the recipient area. Treatment planning must protect existing follicles and consider whether ongoing hair loss could alter the result. DHI may be practical for selected density-enhancement areas because grafts can be placed precisely among existing hairs, but the size of the area, hair characteristics, and surgeon’s technique still matter.
FUE may be suitable when restoration covers a larger region, such as a receding frontal zone combined with crown loss. Its practicality depends on the strength of the donor area, the number of usable grafts, and the patient’s long-term goals. Fine hair, curly hair, limited donor supply, scarring, or poor recipient-site condition can also affect planning.
The key consideration is long-term hair-loss progression. Preserving existing hair and allocating grafts carefully may be more important than choosing a procedure by name. A qualified clinician should assess the donor area, pattern of loss, hair calibre, scalp condition, and likely future changes before recommending DHI, FUE, or a staged treatment plan.
What Should Patients Expect During Recovery and Aftercare?

Recovery after a DHI or FUE hair transplant usually involves a gradual return to normal activity rather than an immediate visible change. In the first few days, the donor area may feel tender, while the recipient area can appear red, swollen, or sensitive. Small scabs may form around the grafts as the skin heals. Patients should protect both areas from friction, pressure, direct sun exposure, and strenuous exercise according to their clinic’s instructions.
Aftercare commonly includes gentle washing with an approved product and avoiding scratching or picking at scabs. Sleeping with the head elevated may help reduce swelling, although the treating provider should give personalized guidance. Mild discomfort can occur, but medication should only be used as directed by the medical team.
Temporary shedding is a possible part of the recovery process. Transplanted hairs may shed before new growth begins, which can make progress difficult to judge during the early months. Visible hair growth develops gradually and depends on factors such as individual healing, graft characteristics, the treatment plan, and ongoing hair-loss progression.
Patients should contact their clinic promptly if they develop worsening pain, spreading redness, significant bleeding, pus-like drainage, fever, or swelling that appears severe or persistent. These symptoms do not necessarily indicate a serious complication, but they require professional assessment rather than self-treatment.
How Can You Choose Between DHI and FUE Hair Transplant?
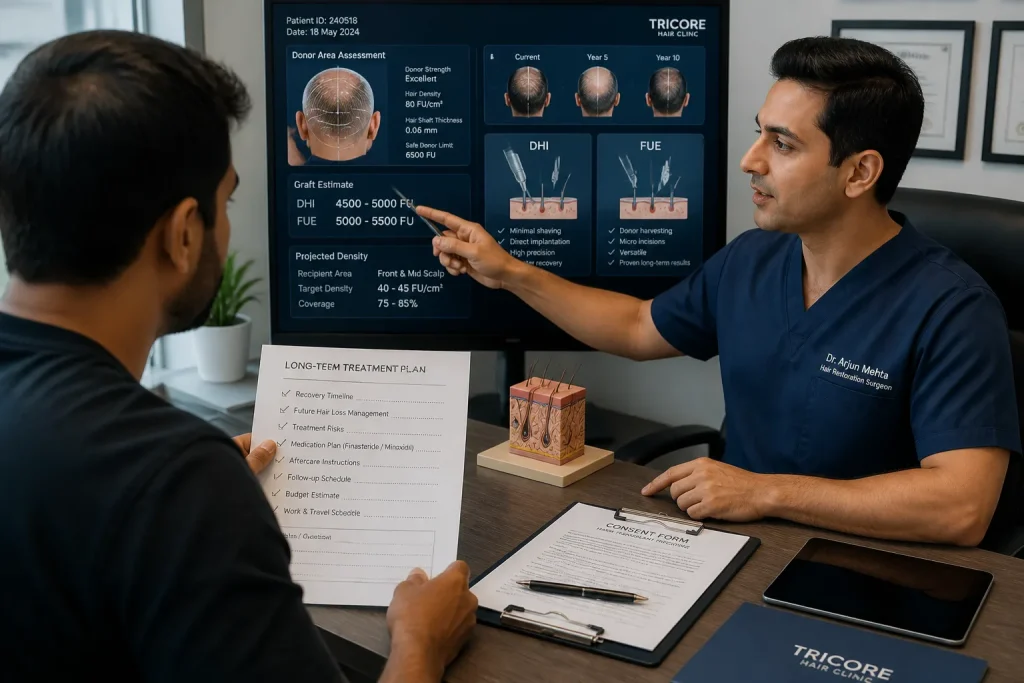
Choosing between DHI and FUE should begin with your diagnosis and long-term hair restoration plan, rather than the technique’s name. A qualified clinician should assess the cause and progression of hair loss, the strength of your donor area, available grafts, scalp condition, and the density you realistically want to achieve.
Your budget, work schedule, tolerance for visible recovery, and preference for a particular implantation method may also influence the decision. However, these practical factors should not outweigh medical suitability. Ask why one approach is recommended, how many grafts may be needed, how existing hair will be protected, and whether future hair loss could affect the result.
Before proceeding, review the surgeon’s qualifications, relevant case examples, treatment planning process, and follow-up arrangements. Discuss possible risks, medication, aftercare, and what happens if growth is uneven or additional treatment becomes necessary. The most reliable choice is the one supported by an individualized consultation and clear explanation of candidacy assessment, not by promotional claims or a promise of guaranteed density.
FAQs
Is DHI less painful than FUE?
DHI is not necessarily less painful than FUE, as both techniques usually involve local anesthesia and cause minimal discomfort during the procedure. Pain and recovery depend more on the surgeon’s technique, the number of grafts, and individual sensitivity than on the method itself. DHI may cause slightly less irritation in some cases because it uses direct implantation, but swelling, tenderness, and tightness can occur with either hair transplant technique.
How long does it take to see hair growth after a transplant?
Most patients notice new hair growth about three to four months after a transplant, although early growth may be fine and uneven. Visible thickening usually develops between six and nine months, with the final result often taking 12 to 18 months as the transplanted follicles mature. Temporary shedding during the first few weeks is normal, but individual recovery varies with the procedure, hair follicles, and aftercare.
Can both techniques be used to increase hair density?
Yes, both techniques can be used to improve hair density, depending on the patient’s hair loss pattern, donor area, and treatment goals. Combining methods such as FUE and DHI may help cover different areas or achieve a more natural-looking result, but a qualified hair restoration specialist should determine whether a combined approach is suitable.



