There is no single, simple answer to who invented the FUE hair transplant. Follicular unit extraction developed through several documented milestones, not as one finished technique at a specific moment. Early work established the idea of removing individual hair follicles from the donor area, while later surgeons refined the instruments, harvesting methods, and placement techniques used in modern hair restoration. This article examines FUE’s origins, the practitioners associated with its development, and how the procedure changed over time. Separating the original concept from later innovations helps readers understand which claims are historically supported and why credit is often shared.
Who Invented FUE Hair Transplant?

The FUE technique does not have one universally accepted inventor, because its history includes an early description, experimental use, and later clinical refinement. The doctor most often credited with introducing follicular unit extraction is Dr. Masumi Inaba, a Japanese dermatologist who described removing individual follicular units with a small punch in the late 1980s. His work established the basic concept of harvesting hair follicles one by one rather than excising a strip of scalp.
However, Inaba’s early reports did not immediately make FUE a mainstream hair restoration procedure. The method was later revisited and formally presented in the 1990s by Dr. Rassman and Dr. Bernstein, who helped define the technique and popularize the term “follicular unit extraction.” Their publications explained how individual grafts could be collected from the donor area and transplanted into areas affected by hair loss.
This distinction explains why different sources give different answers to the question of who invented FUE hair transplant. Inaba is generally associated with the original concept, while later physicians helped turn that concept into a practical, repeatable clinical method. Credit also belongs to the surgeons and researchers who subsequently improved punches, graft handling, implantation, and patient selection.
Therefore, FUE is best understood as a developing technique rather than a single invention attributed to one person. Its modern form emerged through several documented milestones, which shaped how hair follicles are harvested and used in contemporary hair restoration.
How Did Follicular Unit Extraction Develop?
Follicular unit extraction developed through several gradual advances rather than one sudden invention. Early hair restoration surgeons recognized that naturally occurring follicular units could be removed individually instead of harvesting a continuous strip of scalp. This approach aimed to preserve the donor area’s appearance while producing small grafts containing one or more hair follicles.
Early attempts relied on manual punches, but results depended heavily on the instrument’s diameter, sharpness, angle, and depth control. If the punch entered too deeply or followed the wrong direction, it could transect the follicle or damage surrounding tissue. As experience accumulated, clinicians refined punch geometry and extraction technique to improve graft survival and reduce visible trauma.
The terminology also became clearer over time. Individual follicular unit removal was increasingly described as follicular unit extraction, distinguishing it from follicular unit transplantation, the broader process of placing harvested grafts into recipient sites. This distinction helped standardize discussions among surgeons and made the method easier to evaluate clinically.
Clinical adoption expanded as practitioners developed more consistent methods for identifying follicle direction, loosening grafts, controlling bleeding, and storing extracted tissue before implantation. Careful graft handling became as important as the extraction itself, since excessive compression, drying, or mechanical stress could compromise the follicular units.
These milestones transformed FUE from an experimental harvesting concept into a recognized hair restoration procedure. Later developments improved speed, precision, and workflow, but they built on the original principles of individual graft removal, controlled punch use, and meticulous handling.
Which Doctors Advanced Modern FUE Techniques?

Several physicians helped turn FUE into a practical hair restoration procedure, but historical credit is shared rather than assigned to one universally recognized inventor. Their work addressed different challenges, including how to remove follicular units safely, how to improve graft quality, and how to make harvesting more efficient for patients with different donor areas.
Dr. James Harris is widely associated with refining the extraction process and developing instrumentation designed to remove follicular units with less surrounding tissue. His work helped make the procedure more systematic and contributed to the use of specialized punch designs in clinical practice.
Dr. John Cole also played an influential role in promoting FUE and improving its clinical application. His contributions included attention to punch technology, graft handling, and methods intended to reduce damage to hair follicles during extraction. These refinements helped establish FUE as a credible alternative to strip harvesting.
Other hair-restoration surgeons, including Dr. Alan Feller and Dr. Carlos Uebel, contributed to broader clinical adoption and refinement. Their work helped advance surgical planning, donor-area management, and the practical treatment of larger areas of hair loss. Later developments introduced motorized punches and, eventually, robotic assistance, although these technologies represent subsequent innovations rather than the original foundation of FUE.
Professional accounts may differ on which doctor deserves priority for a particular instrument or technique. A more accurate view is that modern FUE emerged through cumulative contributions from surgeons, engineers, and clinical teams. The method used today reflects this progression rather than the work of a single individual.
How Does FUE Differ from FUT Hair Restoration?
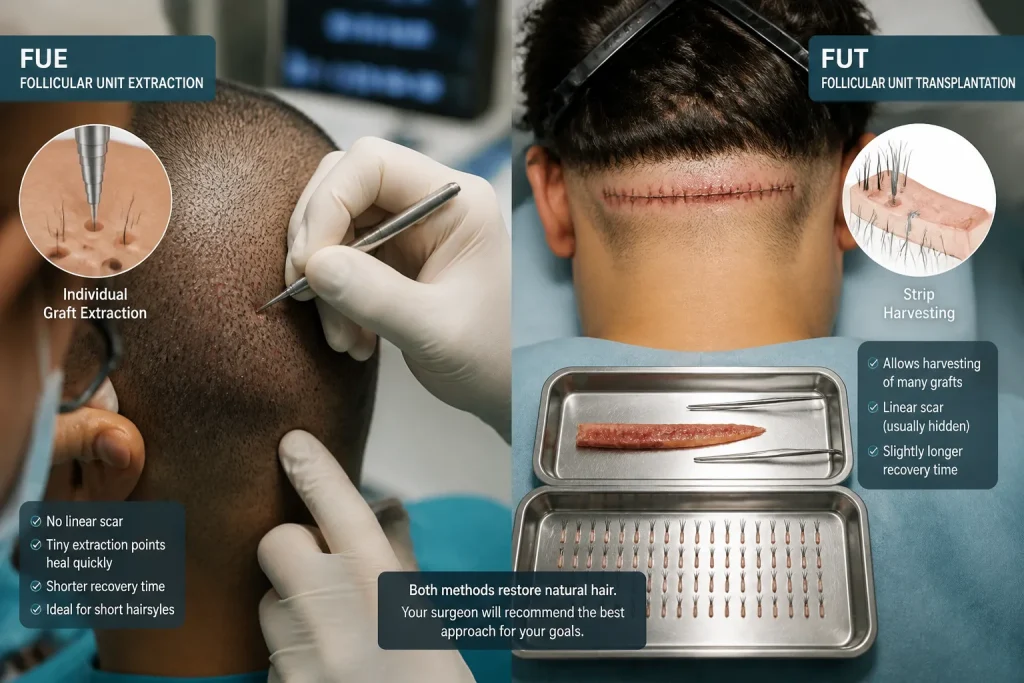
FUE and FUT differ mainly in how donor grafts are collected. In follicular unit extraction (FUE), individual follicular units are removed directly from the donor area with a small punch and then placed into the recipient area. FUT, also called strip harvesting, removes a narrow strip of skin containing hair follicles. The strip is dissected into individual grafts before implantation.
| Factor | FUE | FUT |
|---|---|---|
| Harvesting method | Individual grafts are extracted one at a time. | A strip of donor skin is removed and divided into grafts. |
| Donor-area appearance | Multiple small marks that may be less noticeable with suitable hair coverage. | One linear scar, usually closed with sutures or other wound-management techniques. |
| Recovery considerations | Often involves small extraction sites and may allow comfortable short-hair styling after healing. | Includes healing along the strip incision and may create more tightness during early recovery. |
| Graft handling | Each follicular unit is individually removed and prepared. | Grafts are dissected from the harvested strip under magnification. |
| Suitability | May suit patients who prefer to avoid a linear scar, depending on donor density and goals. | May be considered when a surgeon expects efficient graft collection from a strip harvest. |
Neither approach is universally superior. Donor-area characteristics, hair-loss pattern, available follicular units, hairstyle preferences, treatment goals, and the surgeon’s assessment all influence the recommendation. Recovery and final growth also depend on careful graft handling, recipient-site design, and appropriate aftercare.
What Has Changed in FUE Since Its Early Development?
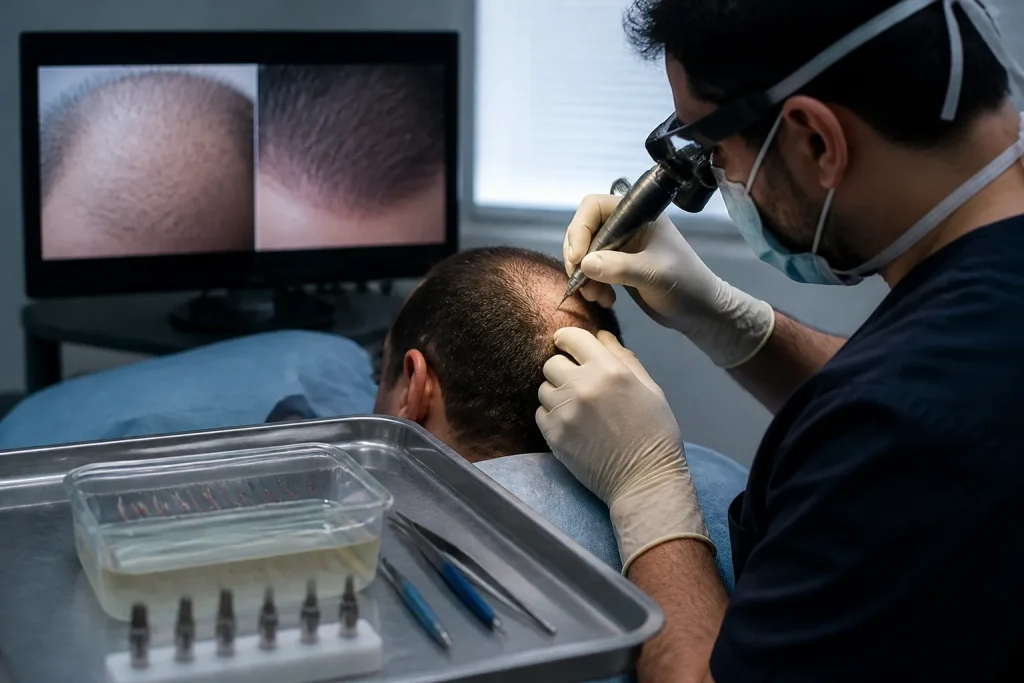
Since its early development, FUE has become more controlled, consistent, and adaptable to individual hair-restoration needs. Early procedures relied heavily on manually operated punches and the surgeon’s tactile judgment. Modern practice may use sharper, smaller, motorized, or specialized punch systems designed to follow the angle and direction of each follicular unit. These tools can support more precise harvesting, although their effectiveness still depends on technique, hair characteristics, and donor-area quality.
Graft handling and preservation have also improved. Clinics now pay closer attention to minimizing time outside the body, maintaining hydration, sorting grafts by tissue quality, and coordinating extraction with implantation. Some workflows incorporate implanter devices, including DHI-style placement, while others use forceps or other insertion methods selected for the case.
Planning has become more individualized as well. Surgeons assess long-term hair-loss patterns, donor reserves, desired density, and the recipient area before designing a conservative extraction plan. Aftercare may include tailored washing instructions, activity restrictions, and medical guidance during recovery. These developments can improve consistency, but newer equipment does not guarantee superior hair growth; clinician skill, patient biology, graft quality, and realistic planning remain decisive.
FAQs
When was the first FUE hair transplant performed?
The first FUE hair transplant was performed in Japan in the late 1980s, with Dr. Masumi Inaba pioneering the individual extraction of follicular units. The technique was later refined and popularized in the early 2000s by Dr. Robert Limmer and other hair-restoration specialists.
Is FUE better than FUT for every patient?
No. FUE is not automatically better than FUT for every patient. FUE typically leaves tiny dot-like scars and may offer a shorter recovery, while FUT can provide a larger number of grafts and may suit some patients with limited donor hair or advanced hair loss. A qualified hair restoration surgeon should assess your donor area, hair characteristics, goals, and medical history before recommending the most suitable technique.
Who can determine whether I am suitable for FUE?
A qualified hair transplant surgeon or dermatologist can assess whether you are a suitable candidate for FUE. They will examine your hair loss pattern, donor area, hair density, scalp health, medical history, and expectations before recommending FUE or alternatives such as DHI or medical treatment.